After its U.S.
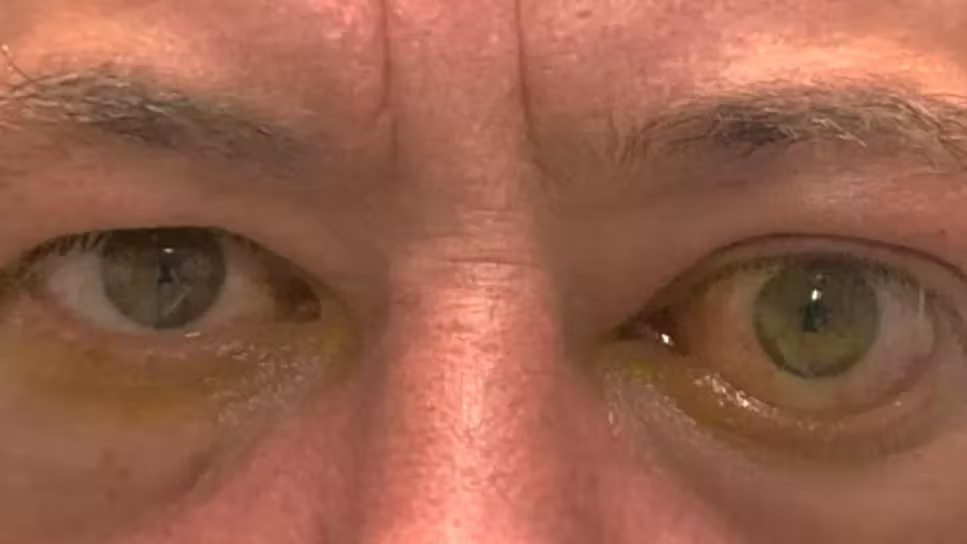
Thyroid eye disease is a chronic autoimmune condition characterized by inflammation and expansion of the extraocular muscles and orbital fat. Symptoms include proptosis, diplopia, eyelid retraction, and, in severe cases, optic nerve compression leading to vision loss. The condition is commonly associated with Graves’ disease, and even in mild forms, it can substantially impair quality of life.
Historically, thyroid eye disease has been characterized by an active phase lasting up to two years, marked by inflammation and progressive tissue remodeling, followed by a chronic, inactive phase in which proptosis and diplopia often persist. Until 2020, treatment options were limited to systemic corticosteroids, orbital radiotherapy, non-specific immunosuppression, and off-label biologics. Relapse requiring retreatment was common, underscoring the recurrent nature of the condition.
Regulatory Approval and Early Clinical Trials
In January 2020, the US Food and Drug Administration approved teprotumumab as the first targeted therapy for thyroid eye disease. As an insulin-like growth factor-1 receptor inhibitor, teprotumumab blocks dysregulated immune responses by interfering with signaling through the insulin-like growth factor-1 receptor and thyrotropin receptor complex in orbital fibroblasts and infiltrating immune cells.
The regulatory approval relied on two randomized, double-blind, placebo-controlled clinical trials. In Phase 2, 69 percent of patients on teprotumumab achieved the primary endpoint of a two millimeter or greater reduction in proptosis, compared with 20 percent on placebo. In Phase 3, 83 percent of patients had a two millimeter or greater proptosis reduction versus 10 percent on placebo. Benefits were also observed across other key outcomes, including clinical activity score, diplopia, and quality of life.
With further evidence supporting efficacy in long-standing and low activity disease, the agency expanded teprotumumab’s indication in April 2023 to include all patients with thyroid eye disease, irrespective of disease activity level or duration.
Real-World Durability and the Reality Check
Despite clinical trial success, extended follow-up and real-world data have introduced a more sobering assessment. A retrospective analysis offers some of the longest follow-up data on patients treated with the medication. The initial proptosis response rate in 21 patients was 84 percent, but it decreased to 57 percent at one year.
Failures did not cease at one year. They continued through the entire two years of follow-up, leaving only about one-third of patients maintaining a sustained response without recurrence. Most patients experienced reactivation of inflammation, measured by clinical activity score regression, and complete loss of proptosis improvement, with levels often returning to baseline. These late flares occurred past the traditional disease activity timeline, suggesting the active phase of the condition could be prolonged in patients receiving the biologic.
The source documents do not provide a quotation from Julian Perry, MD regarding decreased proptosis and vision loss in this context.
These findings align with the concept of treatments functioning either as modulators, which suppress disease symptoms temporarily, or modifiers, which alter the underlying disease course. Because the therapy mainly modulates disease activity temporarily, high rates of relapse and late reactivation highlight the need for medical alternatives that demonstrate a more durable benefit.
Management Guidelines and Side Effect Profiles
Professional societies have established structured frameworks for managing the condition. In 2021, the European Group on Graves’ Orbitopathy introduced guidelines outlining a stepwise approach based on disease activity and severity. For patients with active moderate-to-severe or sight-threatening disease, recommended first-line therapy includes high-dose glucocorticoids and mycophenolate sodium administered concomitantly. Similarly, a joint consensus statement from the American Thyroid Association and European Thyroid Association recommended corticosteroids and orbital radiotherapy as first-line therapy, while teprotumumab is listed as a preferred therapy for moderate-severe active disease when treatment goals include disease inactivation and reduction of diplopia and proptosis.
When patients experience nonresponse or disease flares, interest in a second course of teprotumumab has grown.
Ongoing Studies and Strategic Outlook
As clinical practice moves forward, managing patient expectations and establishing reliable windows for surgical intervention remain central challenges for clinicians.