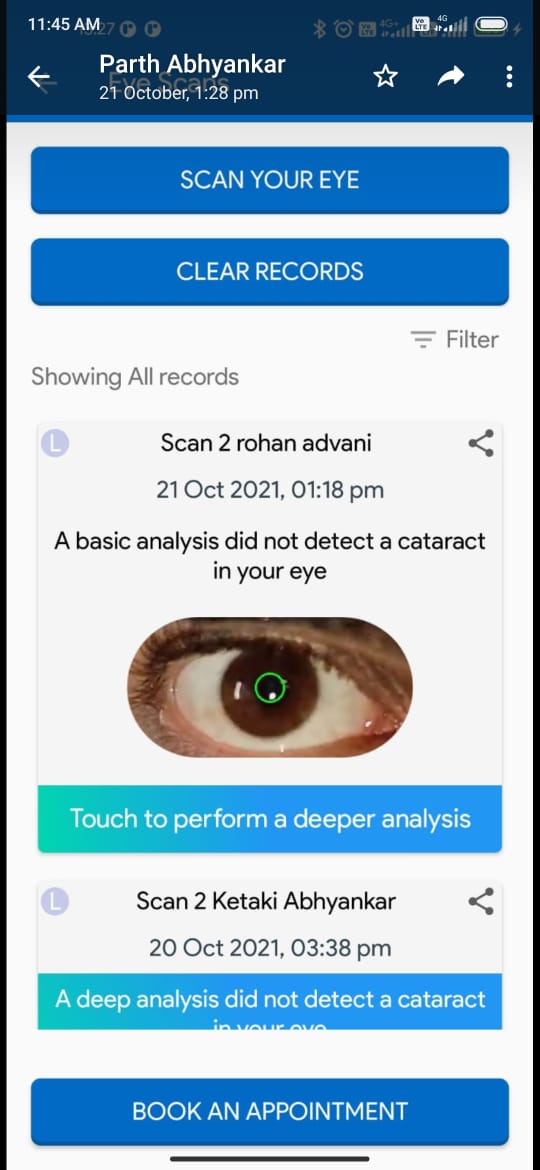
A smartphone-based system for remote cataract screening, developed by Dr. Prabhu Krishna Ravilla at Aravind Eye Hospital, achieved 96% agreement with in-person diagnoses in a study of 1,093 patients, offering a potential solution for rural healthcare access.
Dr. Prabhu Krishna Ravilla, a medical officer at Aravind Eye Hospital in India, presented findings at the 44th Congress of the European Society of Cataract and Refractive Surgeons (ESCRS) that a low-cost smartphone imaging device could revolutionize cataract screening in underserved regions. The device, costing less than £150 (AU$281), enables community health workers to capture diagnostic-quality eye images, which are then reviewed remotely by ophthalmologists. This approach achieved 96% agreement with in-person diagnoses, according to a study conducted in rural Tamil Nadu.
How the System Works
The system uses a portable attachment that clips onto an Android phone, featuring a lens for magnification, LED lights, and a silicone scope to stabilize the device against the eye. Community health workers, trained for three hours, screened 1,093 patients across 19 rural eye camps. Remote ophthalmologists reviewed the images and made referral decisions, which were compared to those of in-person doctors. The results showed 89% agreement on cataract diagnoses, 96% on mature cataracts, and 97% on pseudophakia (eyes with implanted lenses).
These findings challenge the assumption that specialist presence is necessary for accurate cataract screening,
Dr. Ravilla said. They suggest a model where a trained ophthalmologist’s time is used for diagnosis and decision-making—where it is most valuable—rather than travel and in-person examination.
The device’s affordability and ease of use could decouple specialist availability from screening, addressing a critical bottleneck in rural healthcare.
Impact on Rural Healthcare
In India and similar countries, the traditional “eye camp” model—where ophthalmologists travel to rural areas—has been limited by cost, logistics, and specialist availability. An earlier Aravind study found that eye camps screened only 7% of rural residents, with attendance dropping by 80% for those living more than three kilometers from a camp. The pandemic exacerbated these challenges, halting outreach activities entirely.
The new system could enable door-to-door screening, particularly for women, the elderly, and the poorest communities, who are most underserved. For patients, particularly in rural and underserved communities, door-to-door screening becomes imaginable,
Dr. Ravilla noted. The device integrates with existing community health worker infrastructure and operates in low-bandwidth environments, making it adaptable to resource-limited settings.
Challenges and Next Steps
The platform integrates with existing community health worker infrastructure,
he said. It offers a potential path to scaling up cataract screening without a proportional increase in a specialist workforce.