
Researchers at Niigata University identified a new calcium-independent mechanism that triggers podocyte injury in nephrotic syndrome on Thursday.
This mechanism operates independently of the calcium influx typically required for podocyte injury caused by anti-nephrin antibodies, according to Niigata University.
Ephrin-B1 disrupts kidney filtration
The glomerular capillary wall acts as a barrier to prevent plasma proteins from leaking into urine. Podocytes, located at the outer layer of this wall, use foot processes connected by slit diaphragms to maintain this barrier. When these processes are injured, proteinuria occurs, which can lead to kidney failure and increased risks for cardiovascular and cerebrovascular diseases, Mirage News reported.
The research team found that stimulating Ephrin-B1—a protein that binds to nephrin—with an anti-Ephrin-B1 antibody or soluble EphB2 causes both Ephrin-B1 and nephrin to undergo phosphorylation. This process causes phosphorylated Ephrin-B1 to dissociate from nephrin and Par6, another binding protein, News-Medical stated.
Once released from Ephrin-B1, Par6 interacts with the signaling protein Cdc42 to increase its activity. This cascade leads to several cellular changes:
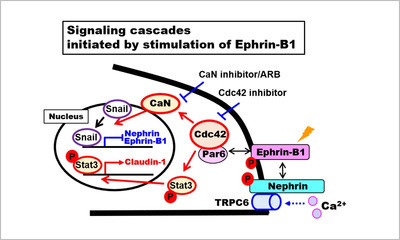
- Increased Cdc42 activity promotes calcineurin (CaN) activity, which alters the regulation of the transcription factor Snail and reduces the mRNA expression of nephrin and Ephrin-B1.
- Increased Cdc42 activity also activates Stat3 independently of calcineurin.
- Activated Stat3 induces the expression of claudin-1, a marker indicating podocyte dedifferentiation.
Potential for new therapeutic targets
The study tested various inhibitors to determine how to stop these signaling cascades. Researchers found that a Cdc42 inhibitor prevented the downregulation of nephrin and Ephrin-B1 expression, as well as the induction of claudin-1, Niigata University reported.
In contrast, while a calcineurin inhibitor and an angiotensin II type 1 receptor blocker (ARB) prevented the reduction of nephrin and Ephrin-B1 expression, they failed to stop the induction of claudin-1. Because of these results, the researchers suggested that targeting Cdc42 may offer a more effective strategy for restoring podocyte homeostasis.
Antibody patterns distinguish different nephrotic syndrome phenotypes
Separate research involving pediatric patients has focused on the role of anti-nephrin autoantibodies in identifying different types of nephrotic syndrome.
In a pediatric discovery cohort of 103 patients, researchers observed different patterns of antibody presence based on the clinical phenotype:
| Clinical Phenotype | Antibody Positivity Rate |
|---|---|
| Steroid-sensitive NS (SSNS) | 100% (77/77) |
| Steroid-resistant NS (SRNS) | 60.0% (9/15) |
| IgA nephropathy (IgAN) | 0% (0/4) |
An independent validation cohort of 42 patients showed similar trends. In this group, high-titer positivity was associated with SRNS in 100% (1/1) of cases, while standard-range positivity was found in 90.9% (30/33) of SSNS cases, medRxiv reported. Antibody negativity in this validation group identified IgAN and membranous nephropathy in 62.5% (5/8) of cases and SRNS in 37.5% (3/8) of cases.
Further analysis of childhood-onset idiopathic nephrotic syndrome (INS) patients indicates that nephrin autoantibody levels may relate to long-term outcomes. In a group of 68 INS patients—consisting of 69% who were steroid-dependent frequently relapsing and 22% who were steroid-resistant—higher antibody titres were observed compared to 26 controls. Specifically, INS patients showed titres of 90.8 (IQR: 46.9-165.4) RU/ml compared to 28.3 (IQR: 20.8-48.0) RU/ml in controls, Frontiers reported.
The study also found that titres were elevated during relapse compared to remission. Among the INS patients, those with minimal change disease (MCD) had elevated titres of 116.1 (IQR: 64.6-210.4) RU/ml. Autoantibody titres were elevated in INS patients compared to controls, Frontiers reported.