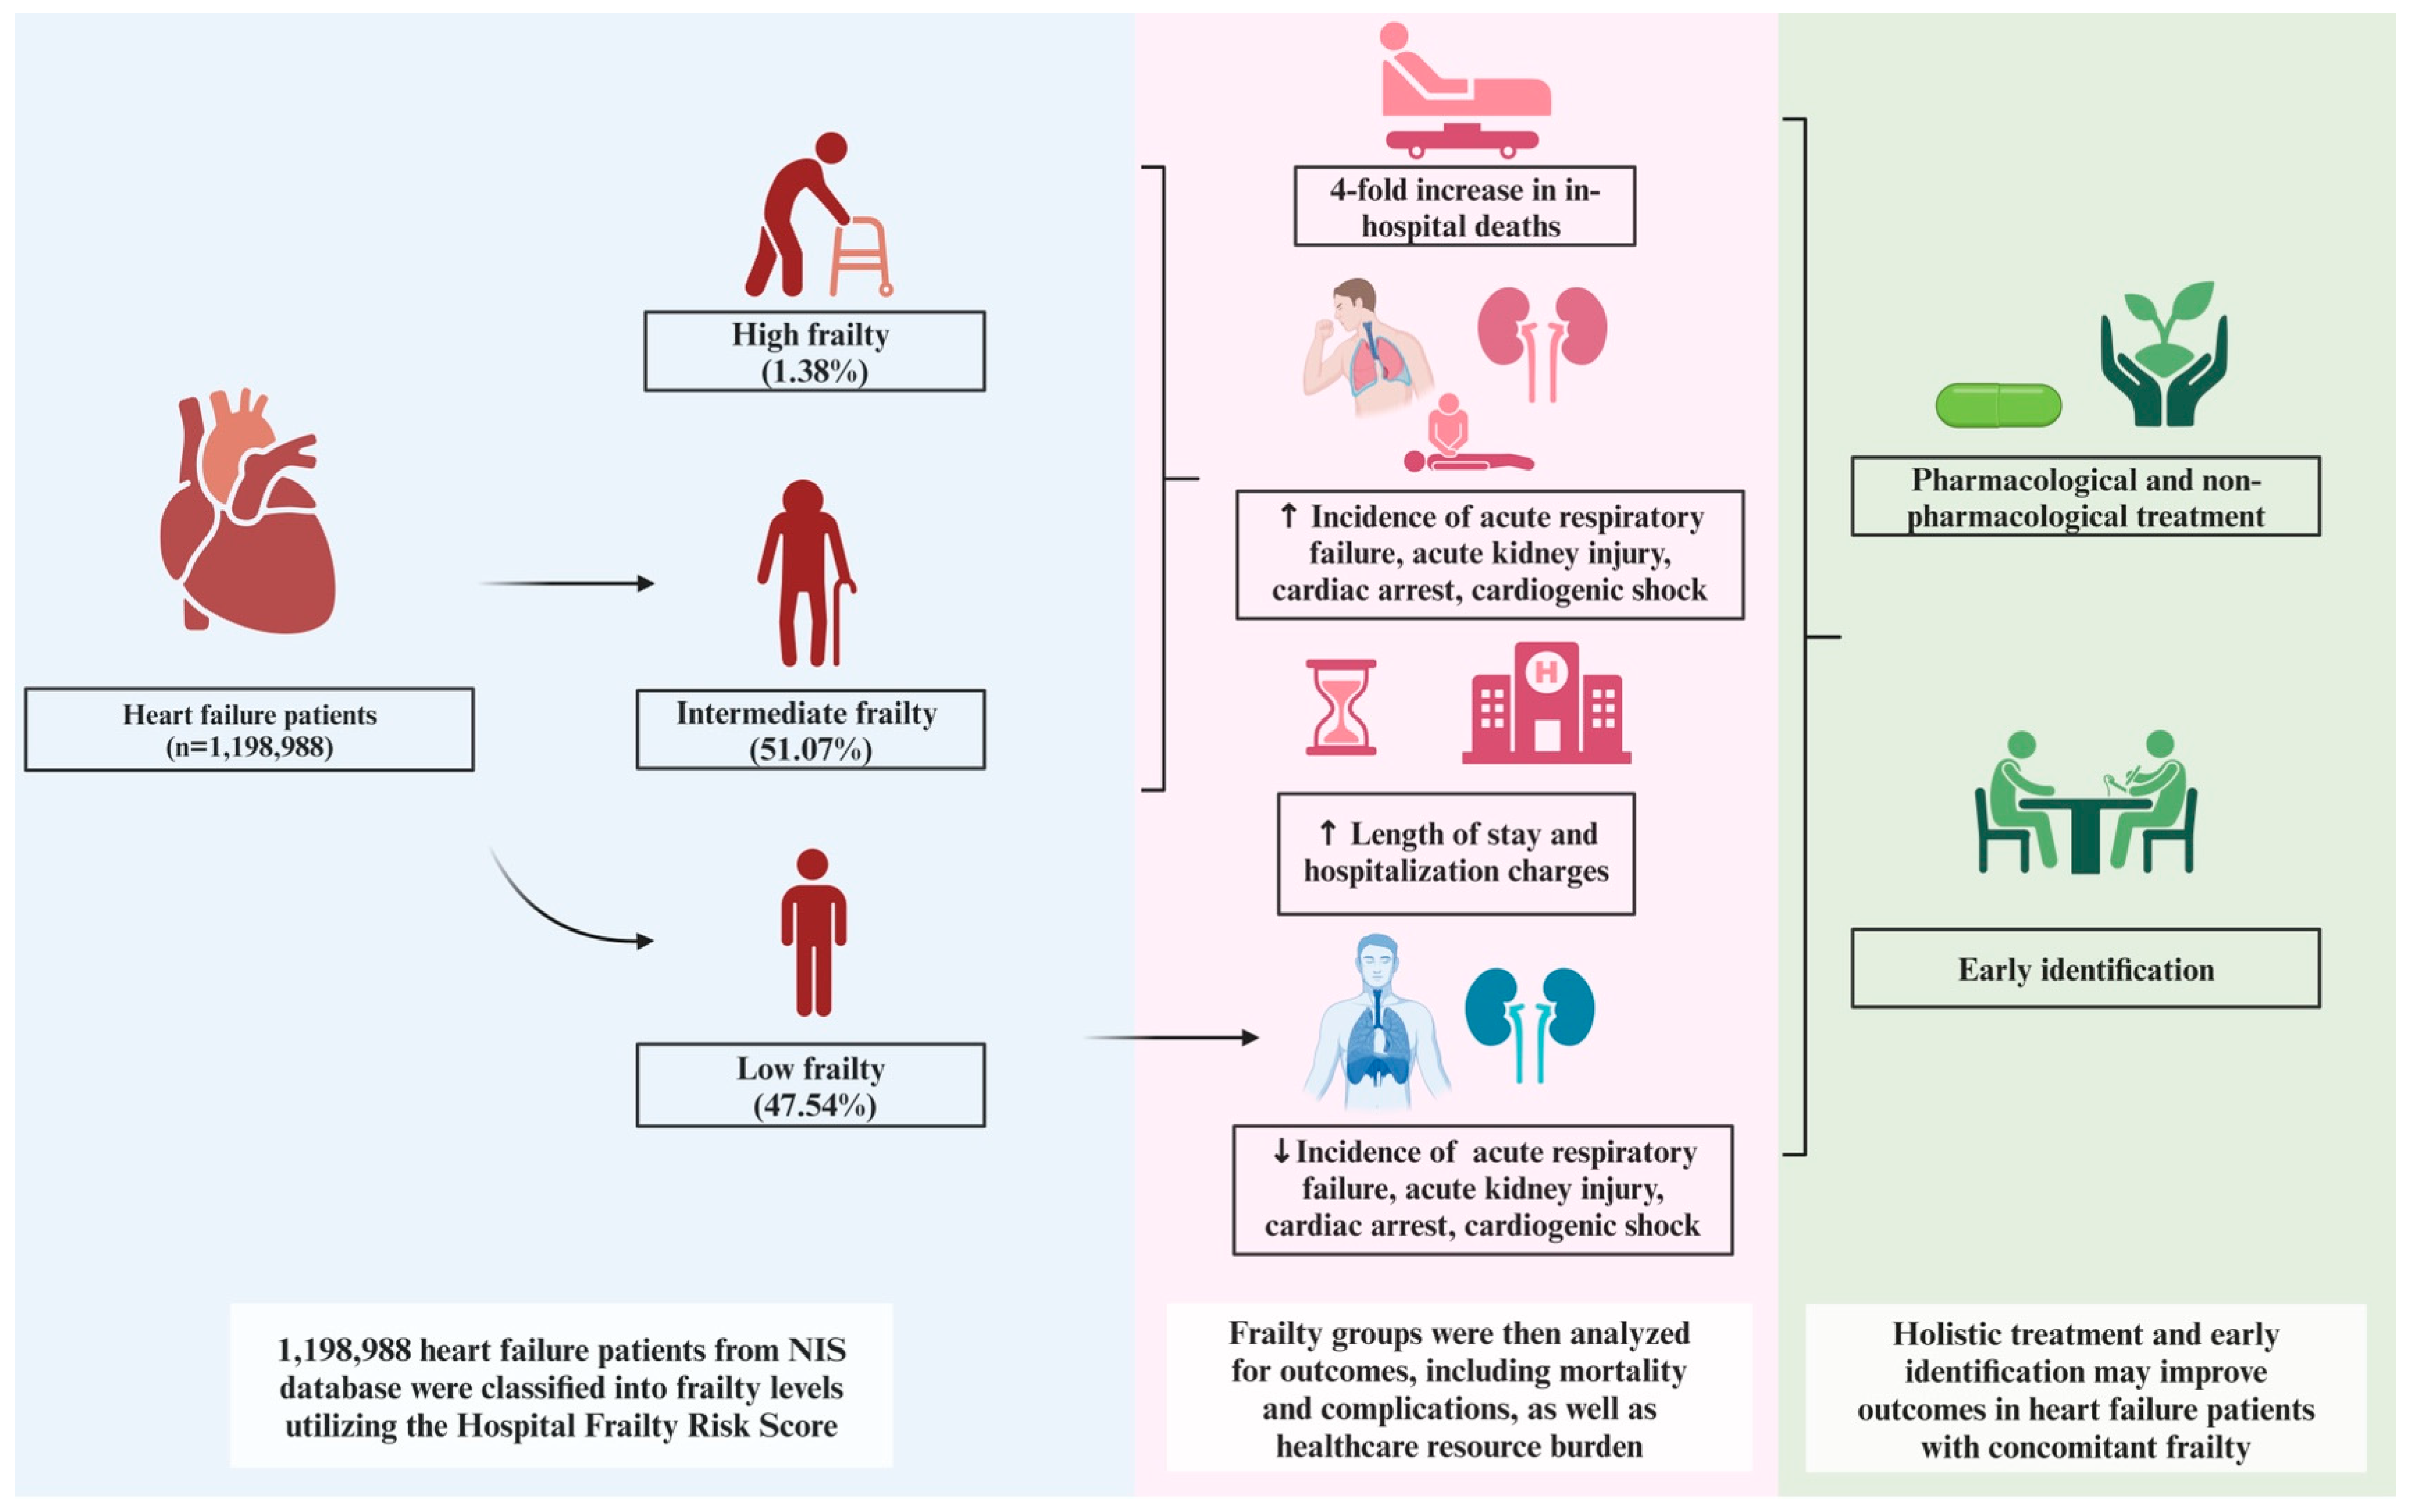
Frailty is increasingly recognized as a critical factor in managing acute heart failure in older adults, according to recent research.
Recent studies highlight the growing importance of Carbohydrate Antigen 125 (CA125) and frailty evaluation in the clinical management of acute heart failure (HF). CA125, a glycoprotein released by mesothelial cells, has emerged as a key biomarker for assessing congestion and inflammation in HF, while frailty scores like the Clinical Frailty Scale (CFS) are critical for risk stratification in geriatric care.
CA125 in Heart Failure: Beyond a Tumor Marker
Originally identified as a tumor marker for ovarian cancer, CA125 has expanded its clinical utility to cardiovascular medicine. According to a review in Cardiac Failure Review, CA125 tracks systemic and right-sided congestion in HF, complementing natriuretic peptides and showing lower dependence on renal function. The study notes that higher CA125 levels identify patients at risk for death and readmission, particularly in patients with preserved ejection fraction and congestion-dominant phenotypes.
CA125’s ability to reflect congestion makes it a valuable tool for guiding decongestive strategies. The review emphasizes that serial CA125 testing mirrors clinical course and response to treatment, with evidence suggesting CA125-guided care has reduced rehospitalisations and improved renal function measures in selected populations. However, the study acknowledges gaps including phenotype-specific threshold, sampling interval, and integration into actionable algorithms.
Frailty in Geriatric Acute Care: Bridging Physiology and Prognosis
A review argues that conventional severity scores like SOFA and APACHE often overlook baseline frailty, leading to limitations in traditional risk stratification. The study discusses the prognostic value of frailty in providing a vital window into the baseline vulnerability of a patient.
The review highlights that frailty assessments, particularly the CFS, have established prognostic value. However, challenges remain, including inter-rater reliability which can vary between clinicians of different specialties or experience levels. The text notes that in rural areas or developing countries, reliable primary care data may be entirely inaccessible, making it difficult to distinguish between a patient’s true reserve and the functional decline precipitated by the current medical crisis.
Converging Pathways: CA125 and Frailty in Geriatric HF Management
While CA125 and frailty assessments address different aspects, CA125 captures two pathways relevant to HF: fluid overload and inflammation, while frailty provides a vital window into the baseline vulnerability of a patient.
The review notes that CA125 has moved from tumour marker to practical tool that refines congestion assessment, improves risk stratification and informs individualised therapy in contemporary HF care.
Addressing Limitations in CA125 and CFS
Both CA125 and frailty tools face limitations. Key gaps for CA125 include phenotype-specific threshold, sampling interval and integration into actionable algorithms. Similarly, the inter-rater reliability of the CFS can vary between clinicians of different specialties or experience levels, and reliable primary care data may be entirely inaccessible in rural areas or developing countries.
>