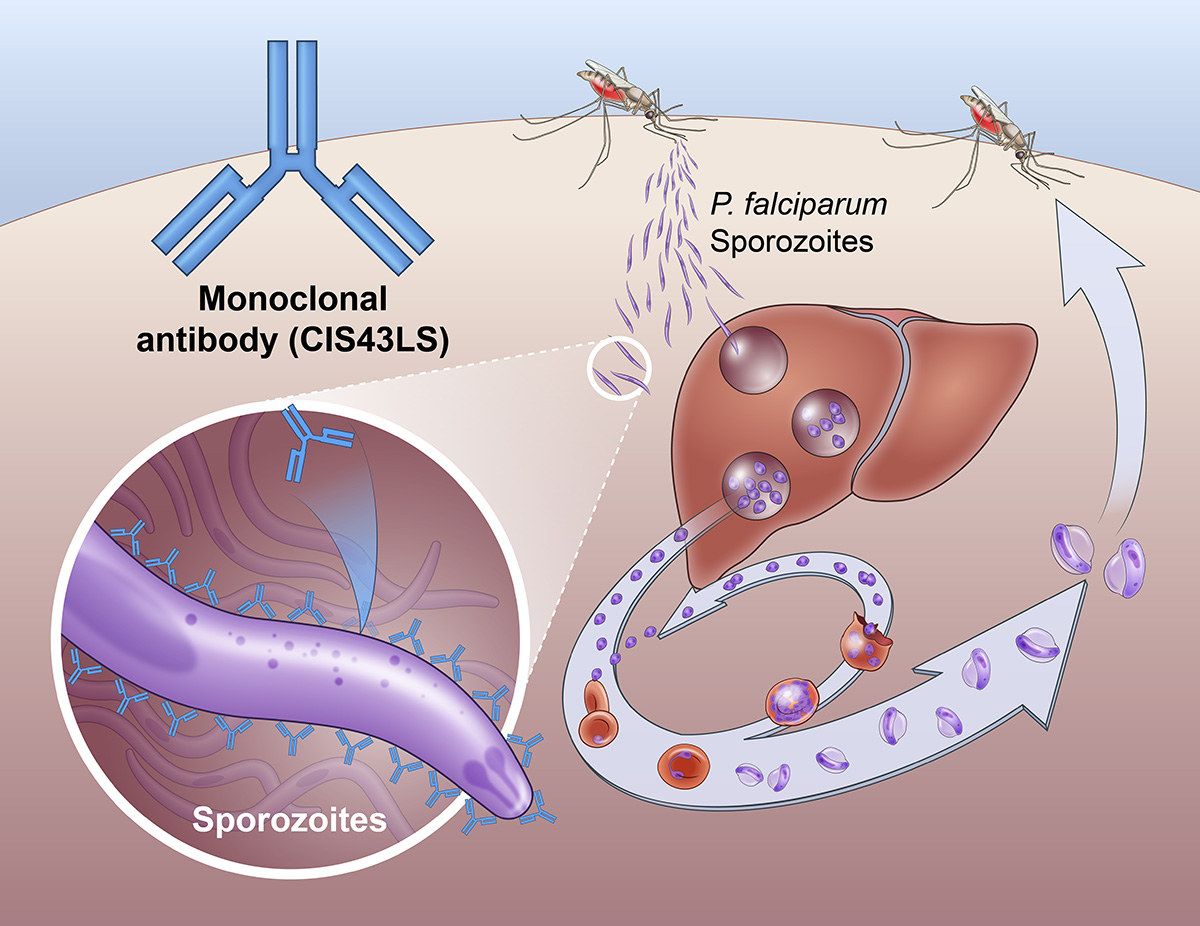
Scientists testing a long-acting monoclonal antibody known as L9LS in infants in Mali found that while it provided strong protection against malaria during the transmission season, it interfered with the immune response generated by the R21 malaria vaccine.
The research detailed recently showed that administering the monoclonal antibody before the vaccine created an issue because both the L9LS monoclonal and the R21 vaccine bind to the circumsporozoite protein, or CSP, on the malaria parasite.
The trial enrolled infants from 1 month to 12 months, giving them either a placebo or the L9LS monoclonal, and then doses of the R21 vaccine. Over the six-month transmission season, testing showed that the monoclonal was 78% effective versus a placebo in providing protection against the malaria parasite, similar to what has been observed in studies of the antibody in older kids and adults.
Public health officials and researchers have held high hopes for the potential of a monoclonal antibody, as one injection can provide recipients with several months of protection against the parasite. Infants might receive an extra barrier of protection from this kind of intervention before they even begin getting the malaria immunizations introduced in recent years.

“In terms of logistics, in terms of programmatical use, this could be a very good tool,” said Kassoum Kayentao, affiliated with the University of Sciences, Techniques, and Technologies of Bamako in Mali and serving as one of the investigators participating in the latest study.
No single cure-all exists for malaria, meaning health authorities must balance the pros and cons of different tactics when selecting which methods to emphasize and for what populations, especially considering the tight budgets surrounding an illness that largely impacts impoverished nations. Approximately 610,000 fatalities resulted from the infection in 2024, with sub-Saharan Africa accounting for most of those who died, predominantly kids below age 5.
The two malaria vaccines, R21 and RTS,S, are considered major scientific breakthroughs as the first vaccines against any parasite, but they require multiple doses to be effective, with the first administered at 5 months of age.
They do provide some level of protection for years. On the other hand, a single dose of a monoclonal can supply several months of defense, potentially lasting long enough to safeguard individuals throughout the highest-risk transmission months.
A main drawback of antibodies is their high cost, though work is underway to cut the price per dose as researchers move into key trials. Specialists said that certain groups could still benefit from a monoclonal antibody and may become the focus of future studies.
Commenting on the findings, André-Marie Tchouatieu from the Medicines for Malaria Venture—who did not take part in the research—remarked that the complications observed between L9LS and the immunization do not restrict how significantly the monoclonal antibody and subsequent generations might lower the overall malaria impact. Tchouatieu recently co-authored a New England Journal of Medicine review outlining the advantages and challenges of different malaria strategies.
“Definitely there will be a use case,” Tchouatieu said.