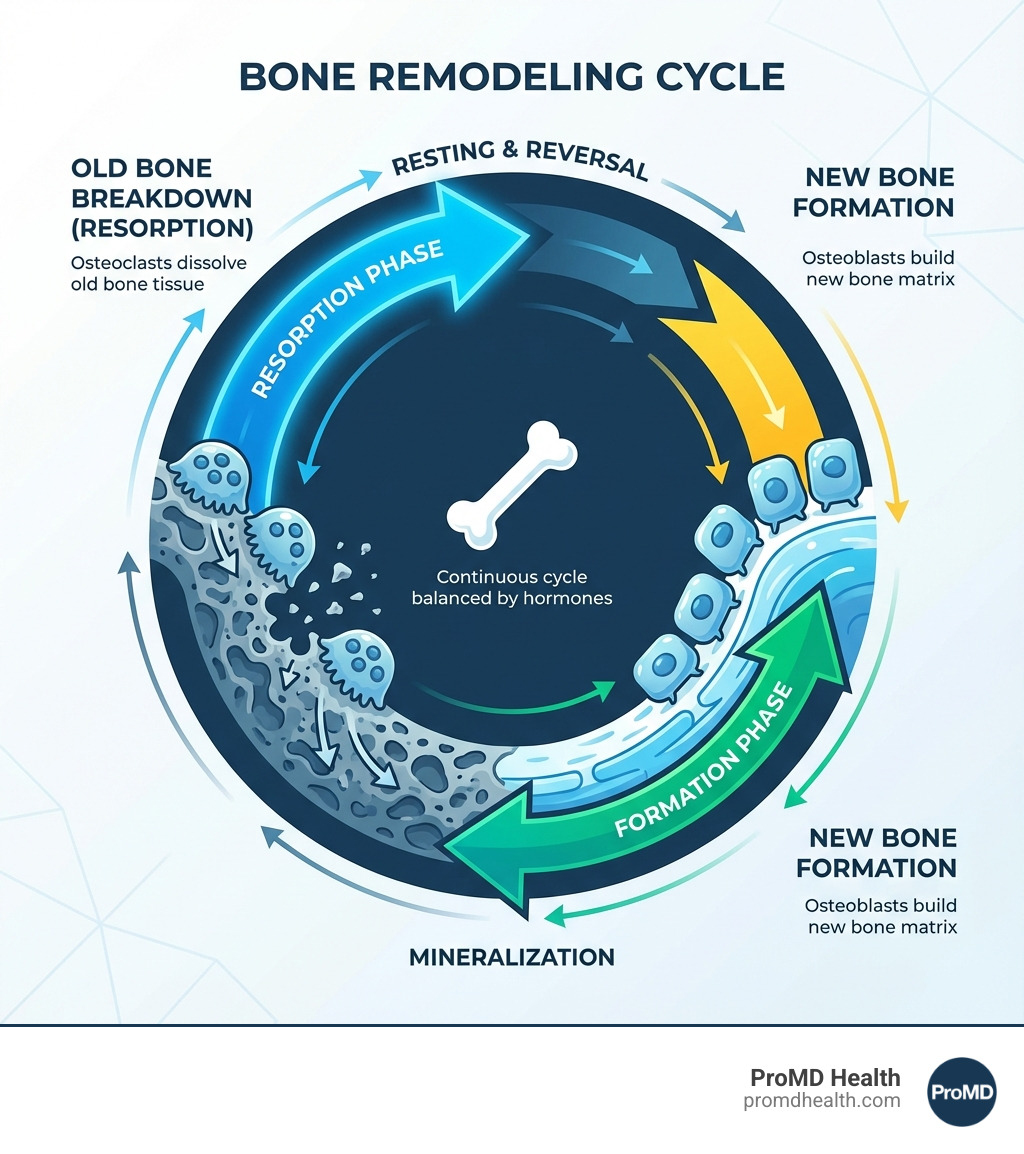
Skeletal integrity relies on a delicate biological balance between bone resorption and formation, a system increasingly recognized as deeply integrated with the immune response through complex cellular signaling pathways involving inflammatory cytokines and receptor systems.
Bone Modeling, Remodeling, and Age-Related Decline
Mineralized bone consists of a protein matrix primarily made of collagen type I fibers coated with a mineral layer of calcium phosphate, largely in the form of hydroxyapatite crystals. During early life, the skeleton forms through endochondral ossification, where bone is patterned in mineralized cartilage before being replaced by mineralized bone. Certain skull bones, such as the calvaria, form directly without a cartilage intermediate through intramembranous ossification.
The skeleton achieves its final shape and load-bearing capacity through bone modeling, which involves the coordinated activity of bone-synthesizing osteoblasts and bone-resorbing osteoclasts. This modeling continues until early adulthood, when peak bone mineral density and bone size are attained. Afterward, the skeleton transitions to a continuous renewal process known as remodeling. During remodeling, osteoclasts and osteoblasts work in unison to clear out damaged or worn bone and resynthesize new tissue, allowing for marrow cavity expansion and increased trabecular thickness. Homeostatically, the rate of osteoclastic resorption matches osteoblastic formation.
In principle, bone remodeling has the capacity to replace approximately 25 percent of trabecular bone and 3% of cortical bone each year. However, this homeostatic regeneration is short-lived. Both men and women begin losing bone mass by their fourth decade of life. Women experience an intensified rapid phase of bone loss for 5 to 10 years following menopause due to estrogen decline, while men undergo a slower, linear loss driven by a progressive reduction in sex steroids.
Fracture Risks and the Impact of Osteoporosis
Persistent age-related bone density loss leads to osteopenia and ultimately culminates in osteoporosis, which significantly elevates fracture risk. Younger males between the ages of 15 and 49 are nearly 3 times more likely to sustain a fracture than females. In older populations, however, fracture incidence is substantially higher among women, affecting roughly one in two older women compared to one in three to four older men.
This gender disparity stems from multiple factors. Women not only lose bone faster after menopause but also accumulate less skeletal mass during growth, particularly during puberty. Consequently, female bones feature smaller diameters and thinner cortices with reduced load-bearing capacity.
The consequences of these fractures can be severe, serving as a notable cause of morbidity and mortality. Vertebral fractures frequently cause intense back pain and disability. Meanwhile, hip fractures routinely demand hospitalization and major surgery, remaining fatal about 20% of the time and producing permanent disability in roughly half of cases.
The Immunoskeletal Interface and the RANKL/OPG Axis
While inflammation has long been known to affect bone turnover, the extent of the centralization between skeletal and immune functions has only recently come into focus. The formation of osteoclasts is centered on the key osteoclastogenic cytokine, receptor activator of NF-κB ligand (RANKL). Numerous inflammatory cytokines promote osteoclast formation and skeletal degradation, but RANKL generally functions as the final downstream effector driving osteoclastogenesis and regulating bone resorption.
The biological activity of RANKL is moderated by its physiological decoy receptor, osteoprotegerin (OPG). Ongoing research into the sources and regulation of both RANKL and OPG under physiological and osteoporotic conditions continues to clarify the complex regulatory networks governing skeletal integrity and its deep integration within the broader immune response.
Neurological Complications and Viral Pathogens
In parallel with systemic and skeletal pathologies, specialized medical literature details complex central nervous system vulnerabilities, including viral encephalitis and meningitis as outlined in neurological reference works edited by specialists such as JD Beckham, MV Solbrig, and KL Tyler. Additional clinical documentation covers polyomaviruses—including JC, BK, and other variants associated with progressive multifocal leukoencephalopathy, BK nephropathy, and Merkel cell carcinoma—as examined by medical authorities like I Cortese, CS Tan, and HH Hirsch across clinical reference texts.
