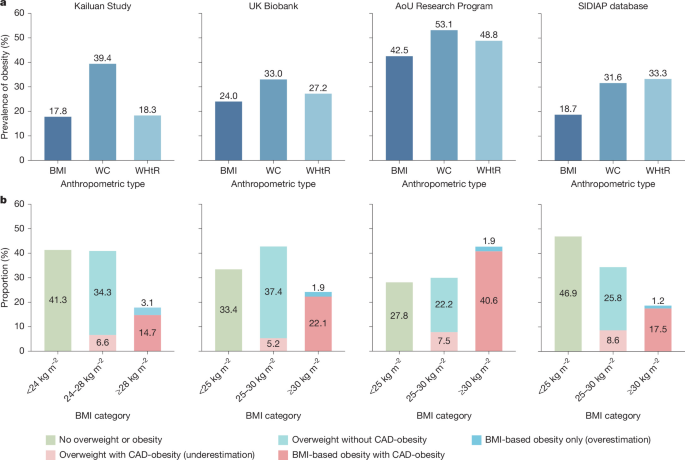
A new international study in Nature published on Wednesday suggests a refined diagnostic framework could identify obesity health risks more accurately than BMI.
Researchers analyzed data from 844,108 adults across China, the United Kingdom, the United States, and Spain.
The study validates an approach that distinguishes between “clinical obesity” and “preclinical obesity.” Clinical obesity occurs where excess fat impairs organ function.
Preclinical obesity occurs where fat poses a risk but organ function remains intact. This distinction helps clinicians separate people with active disease from those who are merely at risk.
“This misclassification can account for tens of millions of people, so the inaccuracy of BMI is a big problem at scale and also for individuals,” said Francesco Rubino, a professor of bariatric and metabolic surgery at King’s College London.
BMI misclassifies millions of patients
Relying solely on BMI can lead to diagnostic errors. According to The Guardian, BMI misses obesity in 5% to 9% of adults.
The metric also wrongly diagnoses the condition in as many as 3% of people. Data in Inside Precision Medicine showed BMI overestimated obesity in up to 3.1% of participants.

The study also underestimated obesity in up to 8.6% of participants across the studied cohorts. The method evaluates 18 different signs of organ or bodily dysfunction, including sleep apnea, joint pain, and cardiovascular disease.
An individual is classified as obese if they have a BMI of 40 kg/m2. Other criteria include a BMI of 30 kg/m2 combined with an elevated waist circumference or waist-to-height ratio. For Chinese populations, the required BMI is 28 kg/m2 or above.
A BMI between 25–29.9 kg/m2 also meets the criteria if paired with both an elevated waist circumference and waist-to-height ratio. For Chinese populations, this range is 24–27.9 kg/m2.
The study predicted overall obesity prevalence would increase by about 3.3% to 7.4% depending on the population. This categorization would label some people with BMIs under 30 as clinically obese due to organ dysfunction.
Some high-BMI individuals would move into a category that does not count as clinical obesity if they lack dysfunction. These multi-criteria measures change how doctors view risk.
Clinical obesity predicts mortality better than BMI
Researchers tracked health outcomes using electronic health records to relate classifications to death. Clinical obesity is a much stronger predictor of mortality than BMI alone.
Live Science reported the clinical obesity classification was better at flagging the risk of death than the traditional metric.
Individuals with clinical obesity had a 69% higher death risk than those with neither obesity nor organ dysfunction. The preclinical obesity group showed a smaller 19% increase in mortality risk compared to those without obesity or dysfunction.
Longitudinal data suggested that the transition from preclinical to clinical obesity is not inevitable for many. Between 77% and 91% of people classified with preclinical obesity did not progress to clinical obesity over a 10-year period. “Midlife is a sensitive period when we consider trajectories of developing negative health outcomes,” said Dr. Jo Blodgett, of UCL’s Division of Surgery and Interventional Science.

“Using the newer Lancet classification in this age group may help identify those at greatest risk of poor health and who would benefit most from intervention.” Blodgett added
“This has a lot of value from a policymakers’ perspective and could save the NHS and its staff time and money,” she said.
The new method adds complexity to the diagnostic process. But Rubino said it allows for more personalized care.
Care could involve lifestyle changes, GLP-1 weight loss medications, or surgery. “We can optimise our interventions and ultimately make better use of our resources with more safety, more efficacy,” Rubino told The Guardian.
“If you ask if I think this should be employed in the clinic, I think absolutely, yes,” he said.
Researchers investigate clinical context
A separate study in the International Journal of Obesity examined data from 7,000 people in the 1970 British Cohort Study at age 46. This research compared BMI with the Lancet clinical obesity framework.

The Lancet framework integrates excess adiposity, functional limitations, and organ dysfunction. Researchers said BMI is a useful screening tool for large populations.
However, the new approach could help direct individualized treatments. More research is required to confirm if the Lancet Commission’s criteria are practical for clinical settings. It is also unknown if they will improve patient care.
Future studies may need to determine if direct measurement of fat provides more meaningful precision. They may also see if it could replace combined anthropometry if reliable bedside technologies become available.
One criticism of the Lancet Commission framework is that distinguishing between obesity types could encourage “watchful waiting.” It could also limit access to treatments.
Researchers said this may conflate diagnostic classification with treatment eligibility.