
A new diagnostic framework published in Nature on Wednesday reveals that body mass index (BMI) misclassifies obesity for tens of millions of people, failing to accurately distinguish between healthy individuals and those at risk of severe health complications.
Limitations of the BMI Scale
Medical experts have long considered body mass index a blunt instrument for defining obesity. By analyzing health records from more than 844,108 adults in the UK, US, China, and Spain, researchers validated a diagnostic approach first proposed in a January 2025 Lancet Commission report.
The study indicates that BMI alone underestimates obesity in 5.2 to 8.6 percent of participants and overestimates it in 1.2 to 3.1 percent. “This misclassification can account for tens of millions of people, so the inaccuracy of BMI is a big problem at scale and also for individuals,” Francesco Rubino, a professor and chair of metabolic and bariatric surgery at King's College London, said.
The new framework aims to provide a meaningful clinical characterization of obesity that can better inform health policy and patient care.
Clinical Versus Preclinical Obesity
The proposed framework moves beyond simple height and weight measurements to include waist circumference and waist-to-height ratio. Under these criteria, a BMI of 40 kg/m² is considered obese, as is a BMI of 30 kg/m² (28 kg/m² or above for Chinese populations) plus an elevated waist circumference or waist-to-height ratio.
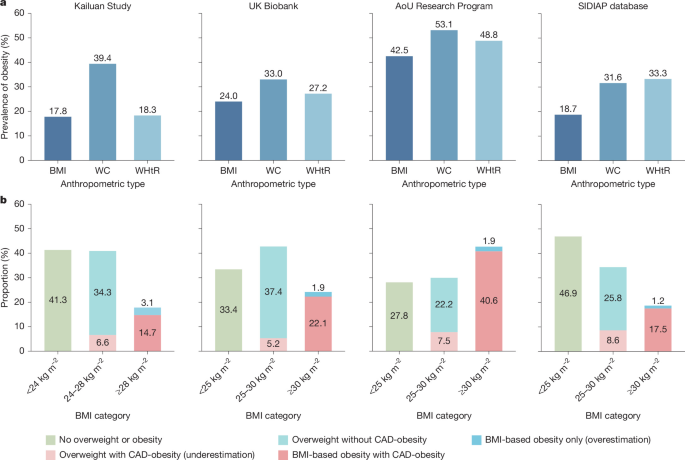
For those with a BMI from 25 to 29.9 kg/m² (24 to 27.9 kg/m² for Chinese populations), obesity is determined by high waist measurements and a high waist-to-height ratio.
- Clinical obesity: An active disease in which excess body fat is already impairing organ function, such as in cases of heart failure or sleep apnea.
- Preclinical obesity: A state in which excess body fat poses identified health risks, but organ function remains intact.
Robert H. Eckel, a physician at the University of Colorado Anschutz who participated in the international research, said that while BMI serves as a useful starting point, it fails to reveal how body fat is distributed or whether it is actively harming a person’s health. He emphasized that these findings reinforce that obesity is not a one-size-fits-all diagnosis.
Impact on Mortality and Treatment
The research showed that the distinction between these categories predicts patient outcomes. Individuals classed as having clinical obesity had a 69 percent higher death risk, whereas those in the preclinical obesity group faced a smaller increase of 19 percent. Over a 10-year period, 77 to 91 percent of individuals with preclinical obesity did not progress to active clinical disease.
“we are definitely missing some people who actually need obesity treatment but just did not meet the BMI criteria,” said Dr. Jennifer Hwang, an instructor of medicine at the University of Chicago.
Rubino argued that this framework allows clinicians to optimize interventions—whether through lifestyle advice, GLP-1 weight loss drugs, or surgery—with greater efficacy and safety.

He said, “If you ask if I think this should be employed in the clinic, I think absolutely, yes.” While some critics have expressed concern that distinguishing between these categories might encourage “watchful waiting” or restrict access to care, researchers said that this conflates diagnostic classification with actual treatment eligibility.
“There needs to be more consensus on what's actually defining clinical obesity,” said Dr. Aayush Visaria, an internal medicine instructor at Rutgers Robert Wood Johnson Medical School in New Jersey.
The study, which tracked health outcomes for up to 15 years, suggests that the new criteria could increase overall obesity prevalence by 3.3 to 7.4 percent compared to BMI alone. Because health states differ in both their clinical characteristics and prognostic implications, the authors conclude that this approach provides a foundation for personalized, proportionate care.
Readers should consult with a qualified healthcare professional to discuss how these diagnostic criteria apply to their individual health status, as these findings are intended for clinical and policy guidance rather than personal medical advice.