
Federal distribution snags and regulatory stalemates are delaying fall respiratory vaccines and monoclonal antibodies across several U.S. states.
Fall respiratory illness season is officially stirring across the United States, marked by rising traffic in emergency departments and familiar strains of seasonal pathogens. Yet Americans attempting to secure early protection face distinct structural hurdles this autumn. Federal disarray has slowed the rollout of crucial fall vaccines and monoclonal antibodies, complicating access for high-risk patients and families according to public health tracking.
Regional COVID-19 Waves and Pharmacy Disparities
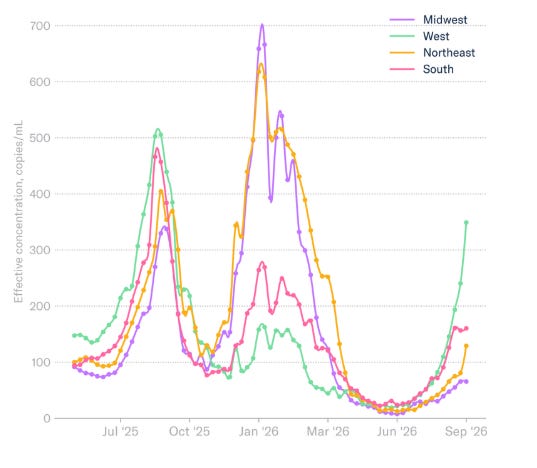
The current COVID-19 data landscape remains intensely region-specific. The West is experiencing an active wave that shows little sign of letting up, while the Midwest and Northeast continue to grow at lower levels than previous winter and summer peaks. Meanwhile, the South appears to have crested after a milder summer surge as indicated by Biobot wastewater data and CDC emergency department metrics.
Despite ongoing viral circulation, accessing updated protection is not uniform nationwide. While most states have decoupled from federal guidance to allow broad pharmacy distribution, adults in a handful of regions—including Louisiana—face immediate roadblocks because state-level vaccine policies conflict with federal retail channels.
Stalled Federal Guidance and RSV Protection Gaps
Respiratory syncytial virus remains a primary driver of pediatric hospitalizations, disproportionately affecting infants under eight months old. However, clinics and hospitals are scaling back orders for protective monoclonal antibody doses because providers fear absorbing out-of-pocket costs if medical insurers refuse reimbursement.
This financial hesitation stems from a broader administrative bottleneck. The Advisory Committee on Immunization Practices (ACIP), operating under federal changes, has experienced complete stagnation in updating its clinical recommendations. Although the American Academy of Pediatrics updated its guidance to reflect emerging science showing broader high-risk infant eligibility, commercial insurers typically follow federal panels. Because federal recommendations remain frozen in past guidance, physicians and families are left navigating ambiguous coverage landscapes.
Pennsylvania Measles Outbreak and the Fourth Fatality
While respiratory viruses strain clinical networks, Pennsylvania has documented its fourth measles-associated death in an active outbreak totaling nearly 800 confirmed cases as reported by state health authorities. This tally marks the most measles deaths in the U.S. since 1992. Standard epidemiological models project that historical fatality ratios of one to three deaths per 1,000 unvaccinated cases suggest an unrecorded community burden numbering between 1,300 and 4,000 total infections, driven heavily by public health hesitancy and underreporting.
The designation of these fatalities as measles-associated has triggered fierce pushback from local officials and medical practitioners. Skepticism centers on whether patients died directly from the virus or merely tested positive while succumbing to independent medical emergencies in a manner reminiscent of historical pandemic-era mortality accounting.
Disputed Diagnoses and Forensic Findings
In Lancaster County, local officials and medical examiners have openly challenged state casualty classifications regarding a deceased newborn. Lancaster County Commissioner Josh Parsons criticized Gov. Josh Shapiro’s administration for withholding demographic details under privacy statutes. Meanwhile, Lancaster County Coroner Stephen Diamantoni publicly disputed the state’s characterization of the infant’s cause of death after conferring directly with forensic pathologists.
Diamantoni noted to regional press that autopsy findings revealed no systemic enlargement or swelling characteristic of acute measles disease, pointing instead to massive internal hemorrhage from a physical injury . Maternal-fetal medicine physician Adam Urato echoed these concerns, arguing that public communications from state leadership misled the public and unfairly burdened grieving families by attributing traumatic birth outcomes entirely to viral infection.
Norovirus Season Arrival and Practical Safeguards
Adding to seasonal pressures, norovirus cases are climbing right on schedule with activity expected to intensify toward an early spring peak. The pathogen presents unique household containment challenges because its protective outer membrane renders it highly resistant to standard alcohol-based hand sanitizers and common surface disinfectants.
Public health guidance stresses that soap, water, and thorough physical scrubbing remain the most effective defenses against transmission via contaminated household surfaces like doorknobs and children’s toys. Individuals experiencing acute gastrointestinal distress are advised to isolate using separate household restrooms and wear masks where feasible to limit intra-family spread while federal agencies work to resolve broader vaccine distribution snags.