
A new analysis published in JNCI: Journal of the National Cancer Institute reveals that overdiagnosis in mammography screening may sit below 5%, challenging older estimates of 30% to 50%. Researchers reanalyzed eight major randomized trials by comparing their temporal patterns against long-term data from Danish population screening programs.
For decades, the public debate surrounding breast cancer screening has wrestled with a difficult paradox. While finding tumors early saves lives, routine mammograms can also uncover slow-growing cancers that would never have caused symptoms or threatened a patient’s life during their lifetime. This phenomenon, known as overdiagnosis, often leads to surgeries, radiation treatments, or hormone therapies for conditions that might otherwise have remained entirely harmless.
Earlier estimates derived from randomized trials suggested that between 30% and 50% of screen-detected breast cancers represented overdiagnosis. These figures heavily influenced international screening guidelines and the information provided to patients. However, a fresh examination of the historical trial data paints a drastically different picture.
Reanalyzing Decades of Trial Data With Danish Registries as a Benchmark
An international research team set out to reexamine evidence from all eight major randomized mammography trials. The scope included historical studies carried out in New York, Malmö, Canada, Stockholm, Gothenburg, Edinburgh, the United Kingdom, and the Swedish Two-County study. By bringing this body of evidence together, the investigators aimed to account for temporal biases that distorted earlier calculations.
To establish a reliable baseline, the team used real-world data from Denmark as a reference population. Organized breast cancer screening began in certain Danish regions roughly 17 years before it rolled out in others. This staggered introduction created a natural experiment, allowing scientists to track precisely how breast cancer diagnoses shifted both at the immediate launch of screening and over the longer term.
Why Early Surges in Cancer Diagnoses Do Not Equal Overdiagnosis
A central insight of the new research involves the timing of diagnoses. When a population-based screening program starts, the total count of diagnosed breast cancers initially rises. Tumors are discovered sooner than they would have appeared if patients waited for palpable lumps or clinical symptoms to manifest.
Many researchers historically misinterpreted that initial spike as proof of rampant overdiagnosis. The new analysis underscores that this view ignores natural temporal flow. Over time, an initial surge in diagnoses should be followed by a noticeable drop, because screening effectively pulls future cancer detections forward.
When screening is introduced, the number of breast cancer diagnoses initially rises because cancers are detected earlier than they would have been without screening. Over time, this should be followed by a drop, as some of these cancers would otherwise have been diagnosed later. This pattern can also be affected if women in either group continue to undergo screening after the trials had ended, which was common.
Elsebeth Lynge, professor emerita at Department of Public Health, University of Copenhagen, via Miragenews
Furthermore, contamination issues in the historical trials complicated matters. Women assigned to control groups frequently began seeking mammograms independently once the trials concluded or as national programs expanded, blurring the statistical boundaries between screened and unscreened cohorts.
Comparing Historical Trials Against Modern Routine Screening
When the investigators aligned identical timepoints across the historical trials and Danish routine screening records, the excess case numbers matched up closely. In Denmark, routine overdiagnosis is estimated to sit below 5%. Consequently, the research team concludes that the randomized trial data are fully compatible with an overdiagnosis rate under 5% rather than approaching 50%.
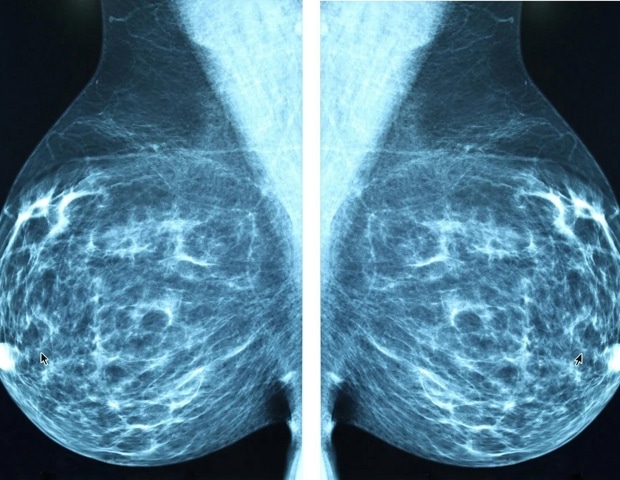
“Taken together, we believe some previous high estimates of overdiagnosis, which influenced screening guidelines and communication, were based on evidence before trial data had fully matured. When interpreted in their full temporal context, randomized trial data are consistent with overdiagnosis of less than 5%, rather than with estimates nearing 50%,”
Matejka Rebolj, Senior Epidemiologist, Queen Mary University of London, via Healthcare In Europe
What the Findings Mean for Patient Decisions and Informed Consent
Accurate metrics regarding screening benefits and harms are vital for patients navigating medical decisions.
Limitations and Unresolved Questions in Modern Screening
Despite the reassuring conclusions regarding overdiagnosis, the authors note that the study relies on a reinterpretation of older trials rather than a fresh randomized experiment.
Instead, it offers a revised lens for interpreting historical data, suggesting that the true harms of overdiagnosis have historically been overstated.