A 72-year-old woman lost her lower leg to a left below-knee amputation following atheroembolic blue toe syndrome stemming from an aortic plaque source, despite attempted endovascular repair, revascularization, and multiple limb salvage procedures, according to a case report published in Cureus.
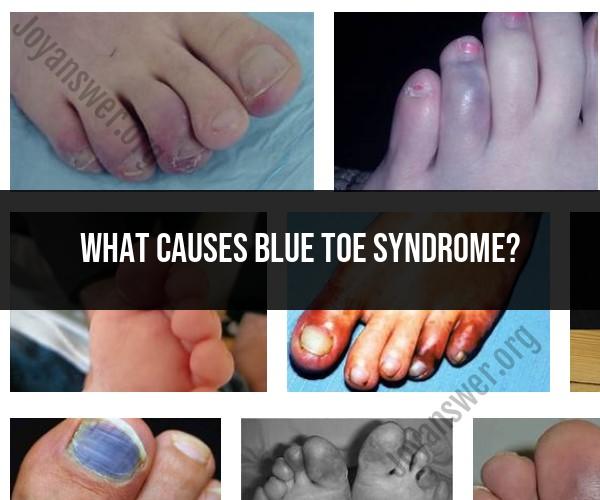
Blue toe syndrome typically presents with a sudden onset of painful blue or violaceous discoloration of one or more toes without major trauma or cold injury. This clinical sign arises when digital arterial perfusion is impaired by vessel-occlusive processes such as vasculitis or cholesterol crystal embolization. In atheroembolic disease, material dislodges from an ulcerated atherosclerotic plaque in a proximal site like the aorta or iliac artery and travels into smaller downstream vessels, producing ischemia in the toes and forefoot area.
Evaluating Aortic Plaque Sources and Distal Runoff Disease
The case detailed by medical researchers writing in Cureus involved a patient with peripheral arterial disease, diabetes mellitus, antiphospholipid syndrome, and prior thromboembolic disease who presented with dusky-blue discoloration of her left third toe. Initial arterial duplex studies showed no major arterial occlusion, while computed tomography angiography with runoff revealed distal infrarenal aortic soft plaque alongside distal tibial and pedal arterial disease.
Medical teams identified the aortic lesion as the suspected proximal embolic source. One of the primary diagnostic hurdles in these clinical presentations is the apparent preservation of proximal large-vessel circulation despite severe distal digital ischemia. Patients often retain palpable proximal pulses, and arterial duplex studies may fail to show major arterial obstruction. Consequently, clinical appearance can appear far more severe than large-vessel imaging suggests, requiring careful evaluation of both the proximal embolic source and the quality of distal runoff to the foot.
Tracking Surgical Interventions and Worsening Complications
To address the proximal source, the patient underwent endovascular aortic repair for source control. Nevertheless, the left third toe progressed to dry gangrene and required amputation. Over the following months, the clinical course deteriorated with nonhealing wounds, worsened distal perfusion, osteomyelitis, and infections involving Pseudomonas aeruginosa and methicillin-resistant Staphylococcus aureus (MRSA).
The medical team pursued numerous limb salvage procedures in an effort to preserve the limb. These interventions included angioplasty, toe amputation, common plantar embolectomy, plantar bypass, transmetatarsal amputation, Achilles tendon lengthening, antibiotic bead placement, and external fixation. Despite these efforts, the foot developed worsening ischemic and infected tissue loss, necessitating an emergency left below-knee amputation.
Pathology Confirms Tissue Damage and Vessel Occlusions
Final pathology confirmed significant tissue damage, including gangrenous necrosis, chronic osteomyelitis, calcific atherosclerosis, and tibial vessel occlusions. The published report highlights that while treating a proximal embolic source may prevent further embolization, it does not guarantee the restoration of distal tissue perfusion when significant distal arterial disease or microvascular compromise persists.
Medical literature characterizes cholesterol crystal embolization syndrome (CES) as a systemic condition triggered when cholesterol crystals from atherosclerotic plaques dislodge into small and medium-size arteries.
Although historical autopsy studies suggest spontaneous atheroembolism has an incidence between 0.79% and 3.4%, and cardiac catheterization-related embolization ranges up to 1.9% for clinically significant end-organ damage, nearly 80% of cholesterol emboli stem from intra-arterial procedures, with abdominal aortic aneurysm repair ranking highest at an approximate incidence of 77%. Management typically centers on supportive care, addressing end-organ damage, and minimizing further embolization by optimizing atherosclerotic risk factors with statins while avoiding anticoagulation unless an alternative indication exists.